

What it is
The contraception mandate sits inside a broader framework for women’s preventive healthcare: the Women’s Preventive Services Guidelines, supported by the Health Resources and Services Administration, or HRSA.
First established in 2011, these guidelines identify services intended to prevent illness, detect problems earlier and support health throughout women’s lives. They are clinical recommendations rather than a separate act of Congress. Their insurance effect comes from the Affordable Care Act, which connects HRSA-supported recommendations to a legal obligation to cover applicable services without patient cost-sharing.
That connection explains why an agency’s decisions about preventive care can directly affect what patients pay.
What it states
The coverage requirement applies to non-grandfathered group and individual health plans, including Marketplace plans and many employer plans. For applicable preventive services, patients generally pay no copayment, coinsurance or deductible when care is provided in network. A service’s age, risk and timing requirements still apply. HealthCare.gov’s coverage explanation describes the general protection.
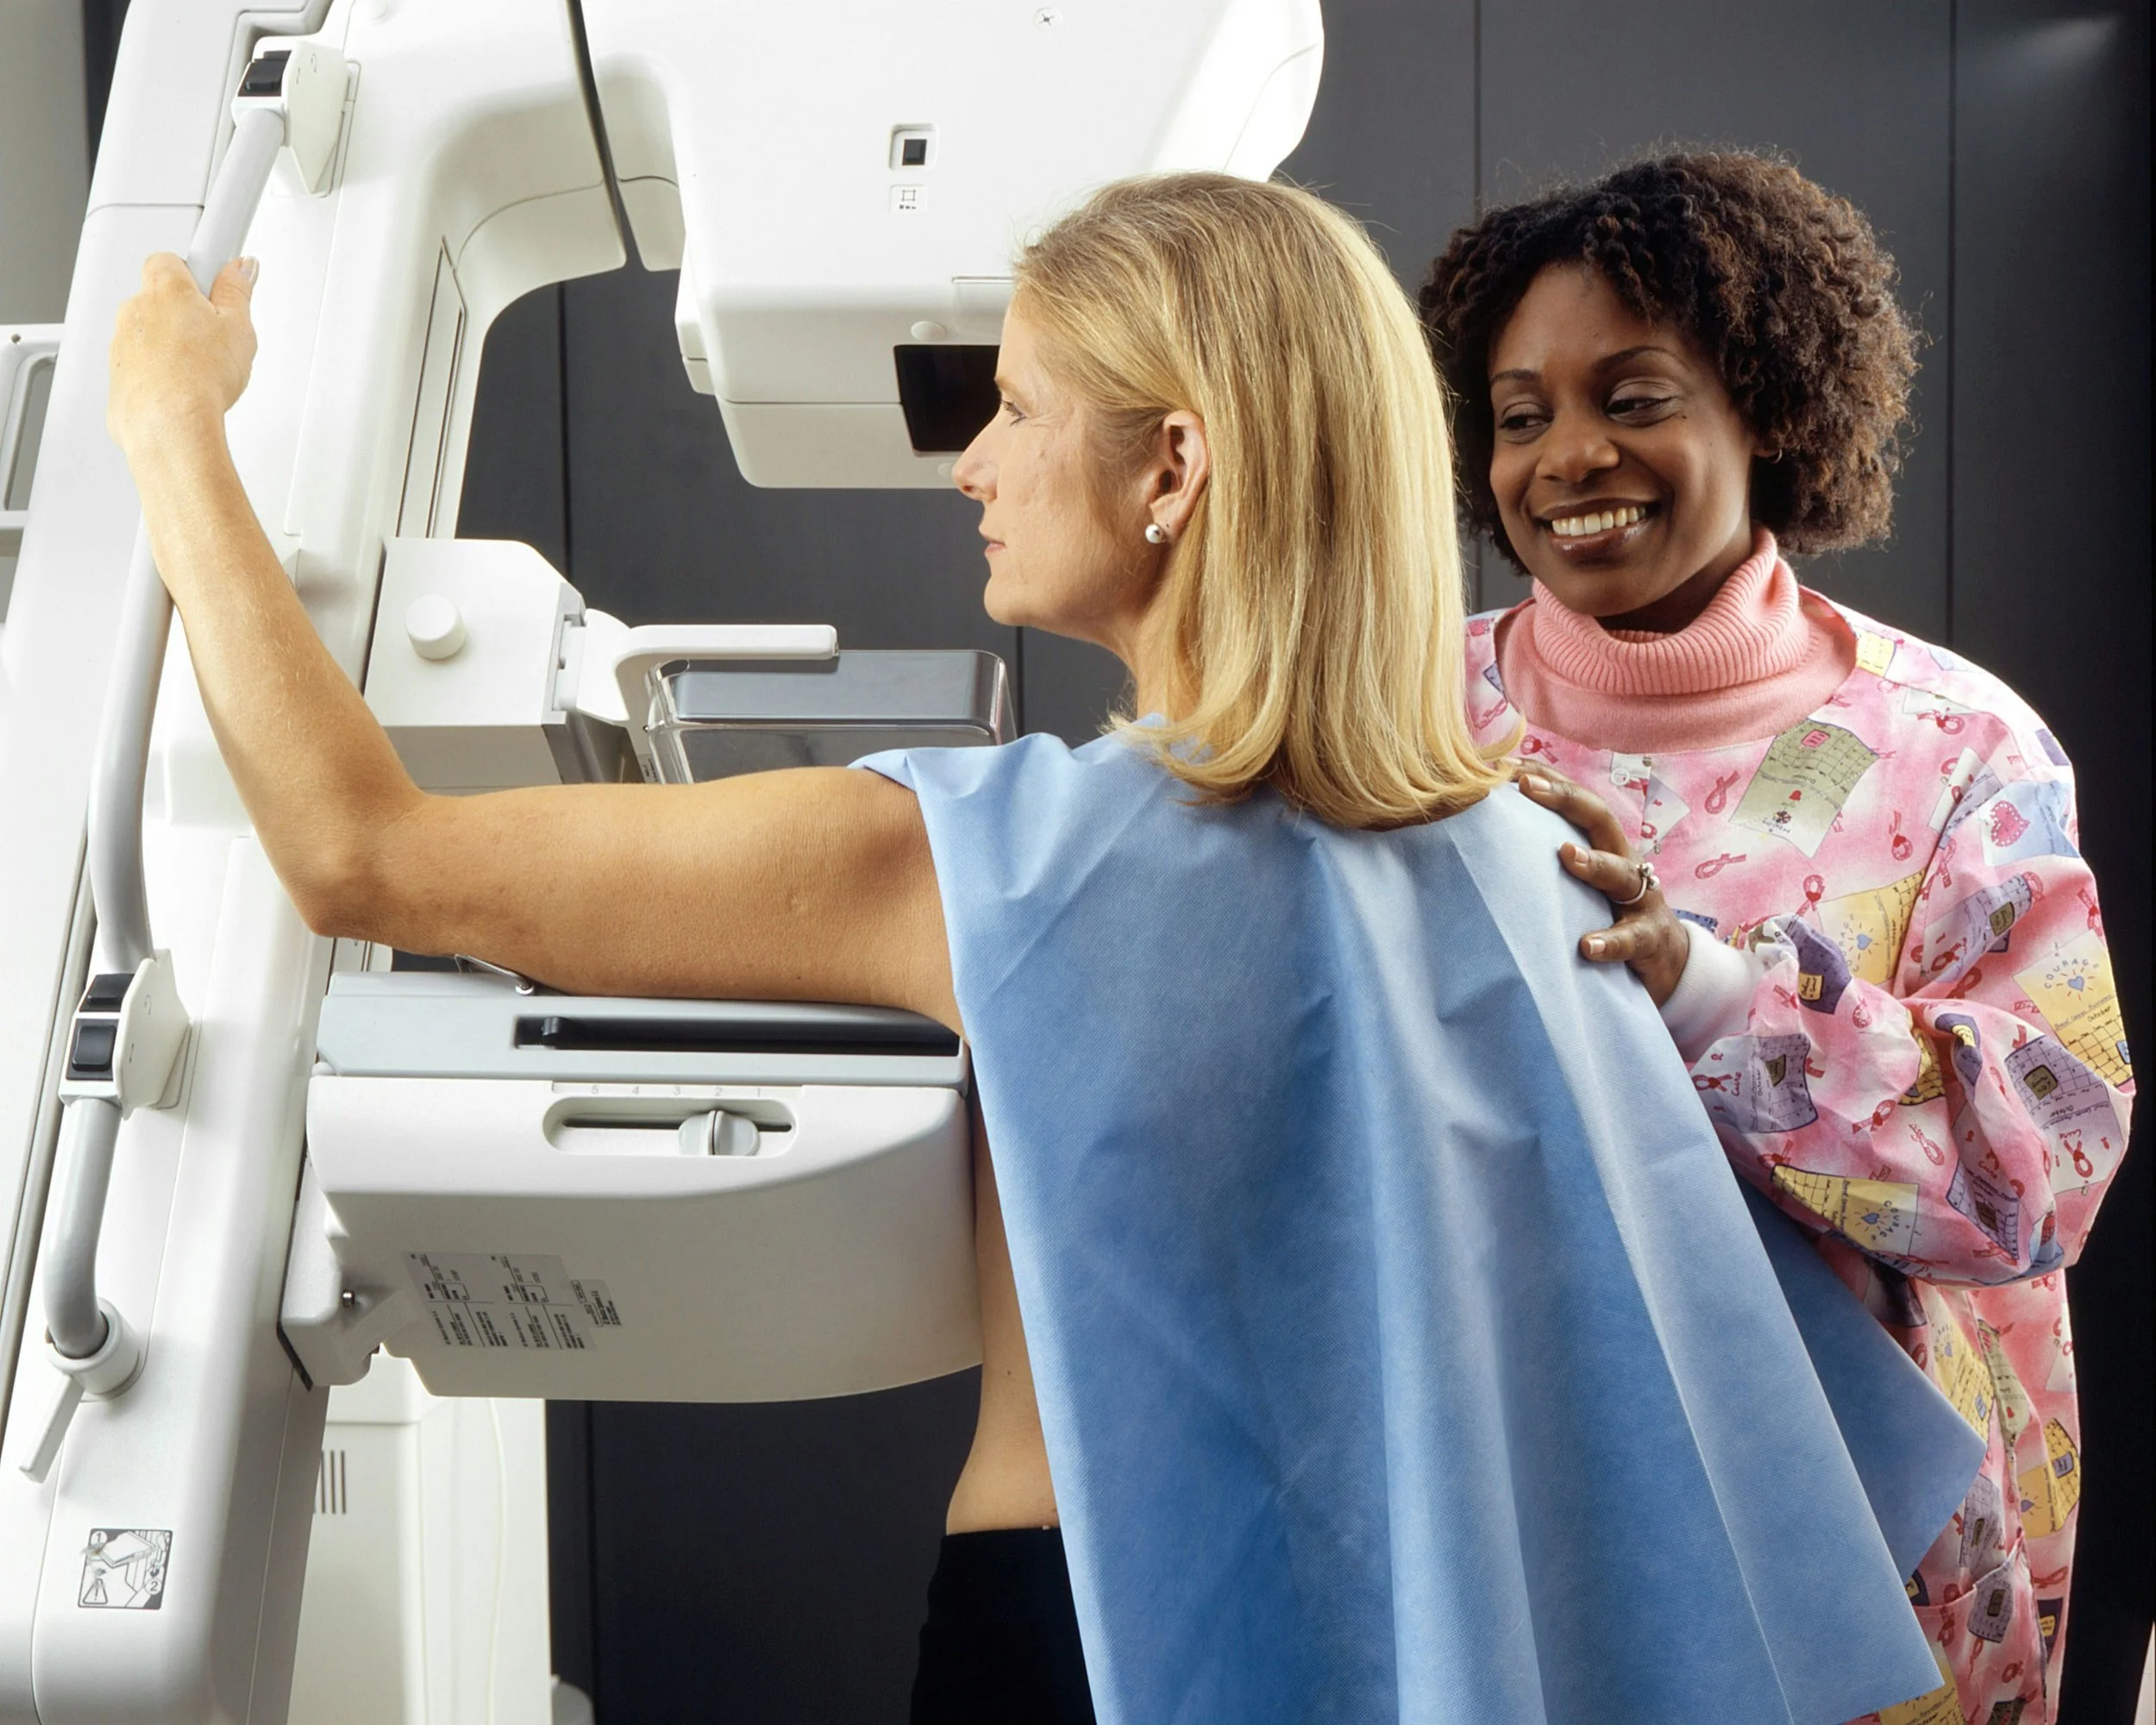
The guidelines extend well beyond contraception. They address well-woman visits, breast and cervical cancer screening, breastfeeding support and supplies, anxiety screening, intimate partner violence screening and interventions, and diabetes screening during and after pregnancy.
An annual preventive visit helps coordinate that care. It does not mean every screening should happen every year: the appropriate services depend on the patient and the particular recommendation.
Who defines preventive care
Congress established the coverage obligation, while HRSA determines the additional women’s preventive services included in its guidelines. Clinical evidence and agency decisions therefore help define the practical scope of an insurance right.
Updates adopted in December 2024 illustrate that process. For most plans, changes taking effect in 2026 include individualized patient navigation for breast and cervical cancer screening and follow-up. Navigation can help patients understand their care, arrange services and connect with support. Updated breast screening guidance also includes indicated additional imaging and pathology evaluation needed to complete screening. The published update explains these requirements.
These changes address an access problem that extends beyond the price of an initial appointment: patients also need help completing the screening process.
Where it stands now
The guidelines remain part of federal preventive coverage requirements. Some older plans retain “grandfathered” status and fall outside this requirement; contraceptive coverage also has separate exemption rules.
Plans can use reasonable medical management when recommendations leave details unspecified. But services integral to providing a recommended preventive service must also be covered without cost-sharing. Federal implementation guidance explains that distinction.
Another cervical cancer screening update takes effect for most plans in 2027. It adds patient-collected high-risk HPV testing as an option for average-risk women ages 30–65 and includes indicated additional testing needed to complete screening. Adoption of a guideline and the date insurers must implement it are separate steps. The January 2026 notice sets out the change.
Why this matters for the rest of the series
These guidelines show how women’s health rights develop after Congress passes a law. Agency decisions determine which services receive protection, clinical recommendations define who qualifies, and implementation determines whether patients receive the promised coverage.
The resulting right depends on several institutions doing their jobs: recognizing preventive needs, keeping recommendations current and making insurers honor the benefits those recommendations create.